
NEWS
Oxford’s Ebola Vaccine Reaches Uganda as Doses Sit Unused
Oxford’s Bundibugyo Ebola vaccine has entered a Uganda trial, but about 620,000 doses remain unused while Congo records 9,415 cases and 4,536 deaths.

Researchers in Masaka vaccinated the first Ugandan volunteers with Oxford’s Bundibugyo Ebola vaccine on 6 October. The same candidate had already gone into a healthy adult in Oxford on 24 July, 68 days after a public health emergency was declared.
About 620,000 doses already sit in Pune, filled in two weeks by the Serum Institute of India. They cannot be used in Congo yet. The shot is still in Phase I, and the outbreak that began in May is now the deadliest Ebola epidemic the country has recorded.
Uganda Starts Dosing Oxford’s Bundibugyo Vaccine
The first volunteers were vaccinated on 6 October in Masaka City, at the MRC/UVRI and LSHTM Uganda Research Unit. The University of Oxford sponsors the study. Professor Eugene Ruzagira, head of clinical research and trials at the unit, is the principal investigator in Uganda, and Professor Simon Drysdale of the Oxford Vaccine Group is chief investigator of that study.
That African arm follows BD-Ebov, the UK trial the Oxford Vaccine Group opened on 13 July. The UK study is testing ChAdOx1 BDBV in 50 healthy adults aged 18 to 55. Professor Katrina Pollock is chief investigator in Oxford, with Professor Teresa Lambe as lead scientific investigator. The first UK volunteer was vaccinated on 24 July, the first time this candidate had been given to a person.
Both trials are funded by the Coalition for Epidemic Preparedness Innovations (CEPI). Uganda has already contained local transmission of this outbreak, Oxford said, and the Masaka site is being used to generate safety and immune-response data while eastern Congo remains the centre of spread. Volunteers in the UK study will be monitored for a year, though researchers expect an early read on immune response and unexpected side effects.
WHAT PHASE I WILL MEASURE
- Safety: Whether healthy adults tolerate the shot, including uncommon reactions that only show up in people.
- Immune response: Whether blood tests show the kind of antibody and T-cell reaction the designers are looking for.
- Not protection: Neither the Oxford study nor the Masaka study tests whether the vaccine prevents infection or disease.
Ruzagira put the limit of this stage in plain terms, because Bundibugyo virus disease still has no licensed shot and no approved drug.
Bundibugyo virus disease is a form of Ebola with no approved vaccine or specific treatment. By evaluating the ChAdOx-based Bundibugyo Ebola vaccine candidate in Uganda, we are generating the evidence needed to determine whether it is safe and capable of stimulating the immune responses that could help protect at-risk communities in future outbreaks.
Professor Eugene Ruzagira, Principal Investigator, MRC/UVRI and LSHTM Uganda Research Unit
If those early studies succeed, CEPI says it expects to work with Oxford and the Serum Institute of India on later trials aimed at emergency use or a licence. That is the step that would matter in Ituri and North Kivu. It has not started.
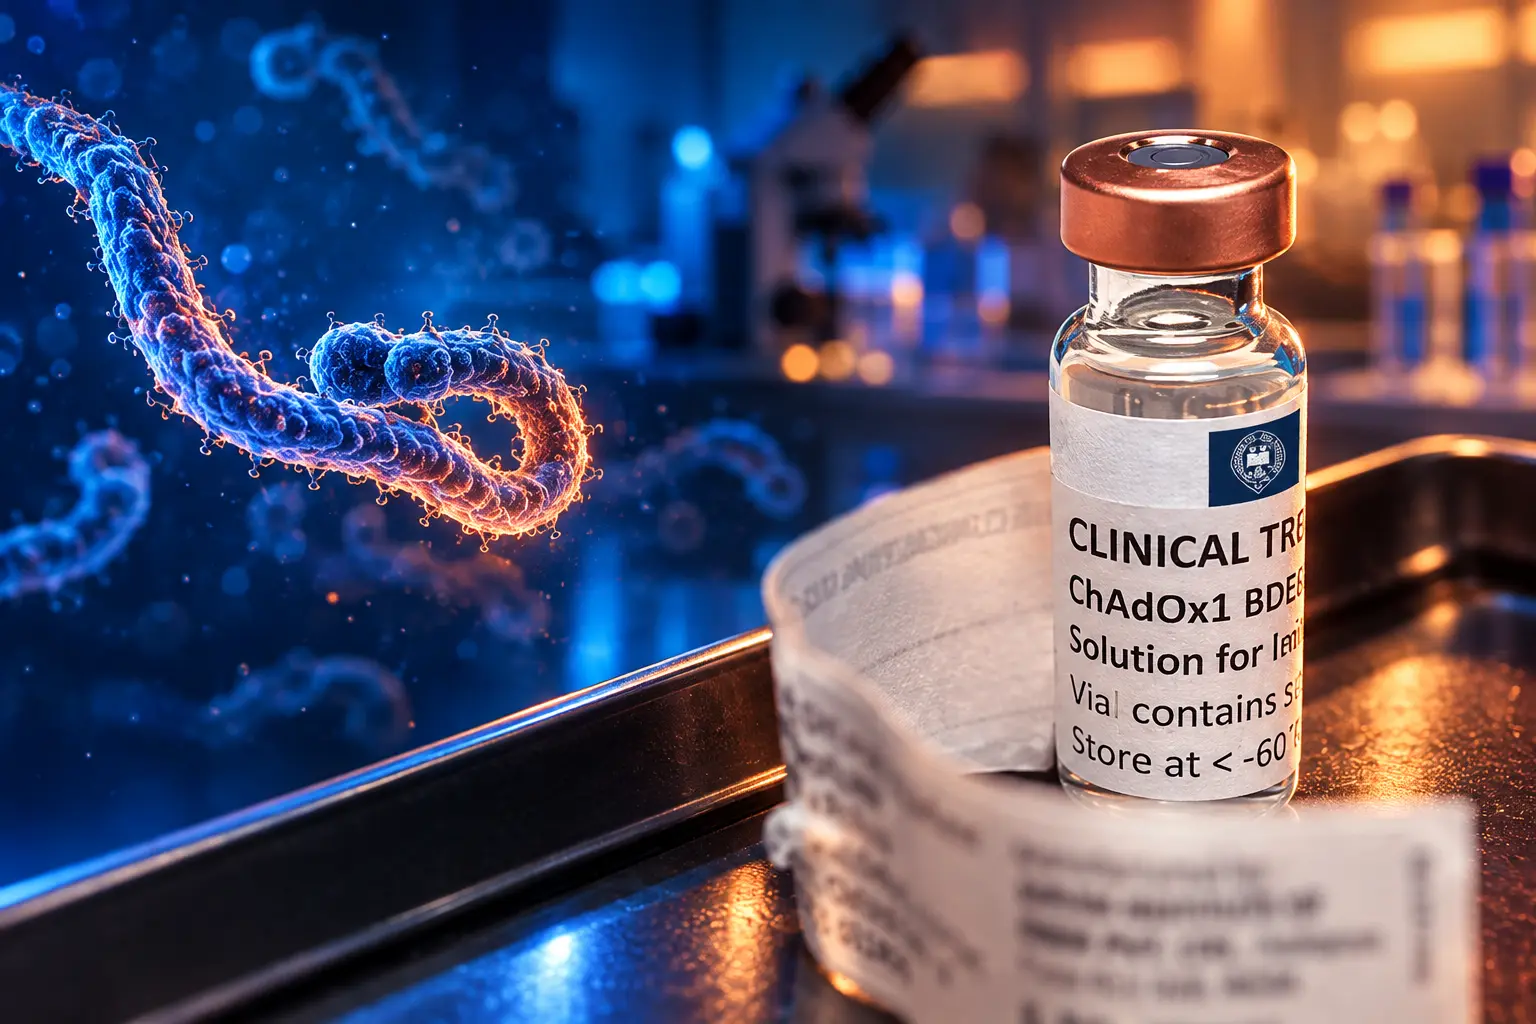
620,000 Doses Were Filled Before Anyone Was Injected
The manufacturing bet is already done. The Serum Institute of India, based in Pune, made and stored about 620,000 doses of ChAdOx1 BDBV in two weeks for possible later trials and emergency use. Oxford’s Clinical Biomanufacturing Facility produced and quality-tested the viral seed stock that the Indian plant then scaled.
CEPI and its partners opened a US$8.6 million partnership with Oxford and the Serum Institute just two weeks after the emergency was declared, building on an existing manufacturing-network tie. The UK Medicines and Healthcare products Regulatory Agency then gave conditional approval for the first-in-human study after mouse and macaque data. SII supplied 4,000 investigational doses for that Oxford trial and about 3,000 investigational doses for the Uganda study.
THE PUNE STOCKPILE
- Filled in two weeks: About 620,000 doses of ChAdOx1 BDBV, held for later trials or possible emergency use.
- UK trial supply: 4,000 investigational doses for BD-Ebov in Oxford.
- Uganda trial supply: About 3,000 investigational doses for the Masaka Phase I study.
- Who paid: CEPI funded Oxford and the Serum Institute through the US$8.6 million programme.
Vaccine researcher Alex Sampson said the group could scale quickly because the work was split across teams rather than queued. “As soon as we heard there was an outbreak, we were able to scale up really, really quickly,” he said. He also said the usual tests were still being done, just in parallel, with groups working around the clock in different places.
Dr Umesh Shaligram, executive director at the Serum Institute of India, said the rapid fill, storage and supply of trial doses showed what collaborators can do when they move together. The doses are still a stockpile, not a campaign. A Phase I product cannot be offered as protection in a treatment centre in Bunia or Beni.
CEPI had already paid to aim this chimpanzee adenovirus, and Moderna’s mRNA work, at Bundibugyo before May. That pre-positioning is why a first human dose could be given in July. It is also why some readers treat the grant calendar as suspicious. A preparedness contract is not evidence that the virus was released. It is the reason the lab phase shrank, and it does not move a frozen crate from Pune into a conflict zone.
Congo’s Deadliest Ebola Outbreak Is Still Untamed
A national situation report covering the 24 hours to 16 October put the Democratic Republic of the Congo at 9,415 confirmed cases and 4,536 deaths. That is a crude case fatality ratio of 48.2%. The same bulletin logged 67 new confirmed cases and 26 deaths that day, 44 of them in Ituri, which remains the epicentre.
The National Institute of Biomedical Research confirmed two cases, including one death, in North Ubangi, on the border with the Central African Republic. That makes North Ubangi the eighth affected province. Dr Nicole Lurie, CEPI’s executive director of emergency preparedness and response, has already called the event the fastest-growing Ebola epidemic on record and the deadliest the country has seen.
The U.S. CDC has said confirmed cases passed 1,000 within 40 days of response activation, compared with about 235 days in the 2018 Congo outbreak of a different Ebola virus. The only larger Ebola epidemic on record is the 2014-2016 West Africa outbreak, which recorded more than 28,600 cases and 11,000 deaths. This one is already the largest ever in Congo, and it is running without a licensed Bundibugyo vaccine.
WHO’s 8 October notice, using data to 6 October, described transmission as still intense and uneven. In the window after its 25 September update, 264 of 372 reported deaths happened in communities rather than treatment centres, a sign people are dying before they reach care. Contact follow-up on 4 October reached 23,741 of 29,535 listed contacts, or 80.4%, under the 85% target. The incubation period runs from 2 to 21 days, and a person is not infectious until symptoms start, which is why missed contacts keep seeding new chains.
On 5 October, WHO was told of a laboratory-confirmed imported case in Kenya. The adult had been ill in Congo, travelled by road to Kampala, then flew into Nairobi on 3 October and died the same day the sample tested positive. Kenyan authorities later identified further infections among contacts already under watch. The Netherlands also received a medically evacuated health worker who had tested positive in Congo. Uganda’s linked outbreak has been contained.
FROM EMERGENCY TO FIRST SHOTS
- 17 May 2026: The World Health Organization declares a public health emergency of international concern for Bundibugyo virus disease.
- 1 June 2026: CEPI funds Oxford and the Serum Institute of India to push the investigational shot toward human trials.
- 13 July 2026: The Oxford Vaccine Group opens BD-Ebov, the first Phase I trial of a Bundibugyo vaccine, in Oxford.
- 24 July 2026: The first volunteer receives ChAdOx1 BDBV, the first time the candidate is given to a person.
- 3 August 2026: Moderna doses its first participant with mRNA-1469 in Truro, Nova Scotia.
- 6 October 2026: The first Ugandan volunteers receive the Oxford shot at the Masaka research site.
Eastern Congo is still a conflict zone with highly mobile communities, which is the setting that made a vaccine feel urgent in May and still does. Isolation, safe burial and basic hygiene remain the tools that actually interrupt transmission while these shots stay in healthy-volunteer studies. A Phase I result in Oxford or Masaka does not close a funeral in Beni.
Why Licensed Ebola Shots Do Not Cover This Virus
Bundibugyo virus was first identified in western Uganda in 2007. Congo’s only previous Bundibugyo outbreak was in 2012. WHO puts the case fatality ratios from those two events at 30% and 50%. The current ratio, 48.2%, sits in that band and is not the milder picture sometimes attached to this species from the 2007 numbers alone.
There are six Ebola species, often described as sisters rather than twins: similar enough to be grouped, different enough that they need their own shots and drugs. Ervebo, the licensed emergency vaccine used against Zaire ebolavirus, does not cover Bundibugyo. That is why responders this time started with no approved vaccines or specific treatments.
Zaire shots sitting in a global emergency stockpile cannot be treated as a Bundibugyo campaign. Some groups have discussed testing whether the Zaire vaccine gives any cross-protection, and doctors in Ituri have opened treatment studies, including antibody and antiviral arms. That is not a licensed Bundibugyo product. Until a species-matched shot finishes human testing, each new sister still forces a fresh construct.
That is the structural bind behind the eight-week lab sprint. The chimpanzee adenovirus shell can be retargeted in weeks. Licensure cannot. Manufacture-at-risk can fill 620,000 vials before the first volunteer rolls up a sleeve. It cannot skip Phase I because the insert is new, and it cannot run a proper efficacy trial from a UK clinic while the epidemic is in a war-affected province.
A Chimpanzee Cold Virus Carries the New Insert
ChAdOx1 BDBV uses the same viral-vector method as the Oxford/AstraZeneca Covid vaccine, which Oxford estimates saved around six million lives in its first year of use. A common-cold virus that infects chimpanzees is genetically altered so it cannot copy itself as a normal infection. That shell is the envelope. For Covid, the insert was a snippet of coronavirus code. This time the insert is a snippet from Bundibugyo virus, enough to make one viral surface protein inside human cells.
The shot does not cause Ebola. The protein is there to teach the immune system what to look for, so the body has a head start if it later meets the real virus. Pollock has said her group runs Phase I trials of new vaccines all the time, “precisely to be ready for exactly this kind of outbreak.” The speed, in other words, was the point of keeping the shell on the shelf.
The same shell carries a known rare risk. The Oxford Covid vaccine was restricted in some countries because of unusual blood clots that affected up to one in 100,000 people. Pollock said severe side effects are “very rare,” that the team thought “very deeply” about putting a new construct into healthy volunteers, and that any risk would be explained to them. “I want to stress that the Covid AstraZeneca vaccine was given to millions of people safely,” she said. Bundibugyo disease in this outbreak is killing about 48.2% of confirmed patients, which is the comparison the investigators are using when they talk about that clot figure.
The Bundibugyo ebolavirus outbreak raging in the DRC is now the fastest-growing Ebola epidemic in history. We urgently need a safe and effective vaccine that could help bring this crisis to an end.
Dr Nicole Lurie, Executive Director of Emergency Preparedness and Response, CEPI
Lurie’s next sentence, on the Uganda study, was that its findings are needed to move ChAdOx BDBV to the next stage of testing. That is the whole gap in one line: the epidemic is already the country’s worst, and the matched shot is still collecting safety bloods.
Moderna’s Shot and an rVSV Candidate Remain Early
Oxford’s construct is not the only Bundibugyo shot in people, and it is not the one some agencies have called the most promising on paper. Moderna’s mRNA-1469, which packs instructions for the same Bundibugyo surface protein in a lipid particle, entered a first-in-human trial on 3 August in Truro, Nova Scotia. That Canadian study aims for about 80 healthy adults and, like Oxford’s, measures safety and immune response, not whether anyone is protected. CEPI committed up to US$50 million to Moderna’s preclinical work, Phase I, and trial-dose manufacture. Africa CDC said the candidate received ethical approval on 7 October for a Phase Ib trial in Uganda; first enrolment there has not been reported.
IAVI is building an rVSV construct, the same vesicular stomatitis virus method behind Ervebo, swapped onto a Bundibugyo glycoprotein. WHO has described that single-dose idea as the most promising Bundibugyo candidate in development, while estimating it is still seven to nine months from human efficacy trials. CEPI put up to US$3.2 million into that work, then up to US$8.5 million for Hilleman Laboratories in Singapore to make trial doses from IAVI seed, with MSD advising on the rVSV process.
BUNDIBUGYO VACCINE CANDIDATES NOW IN TESTS
| Candidate | Who is making it | Method | Status |
|---|---|---|---|
| ChAdOx1 BDBV | Oxford and Serum Institute of India | Chimpanzee adenovirus | Phase I in Oxford and Masaka |
| mRNA-1469 | Moderna | mRNA | Phase I in Canada since 3 August 2026 |
| rVSV-BDBV | IAVI, with Hilleman manufacturing support | Vesicular stomatitis virus | Not yet in people; 7 to 9 months from efficacy trials |
None of these products is approved. The Oxford shot is first into Africa, first into a stockpile of this size, and still not a tool the Ituri response can draw like Ervebo was drawn in Zaire outbreaks. If Phase I holds, CEPI says it will back the late-stage studies that stand between Pune’s freezer and an emergency listing. Congo is already on 9,415 confirmed cases. The vials are already filled. The missing step is the one that takes months, not weeks.
Disclaimer: This article is news reporting and analysis of an ongoing outbreak and of investigational vaccines. It is for information only and is not medical advice, vaccination advice, or a recommendation to seek or refuse any shot, trial place, travel plan, or treatment. Readers who have symptoms, possible exposure, or questions about Ebola vaccination or trial enrolment should speak to a qualified physician or local public-health authority before acting. Case counts, death totals, trial status, and regulatory decisions are taken from the named agencies and study teams and can change as new situation reports and trial notices are issued.

Europe’s Heat Killed 50,391 in Cities Official Counts Still Miss

Caesarean Surge Puts 20 England Maternity Units at Risk

The Protective Ring Around Care Homes Never Existed

Cooper Prioritises Children’s Corridor Care Without an Age Count

Oxford’s Ebola Vaccine Reaches Uganda as Doses Sit Unused

Pennsylvania Measles Deaths Collide With Falling MMR Coverage

Muscle-Boosting Drugs Near Approval for Children With SMA

FDA Approves XFG COVID Vaccines While the Advice Panel Is Frozen

Progranulin and JAK2 Split the Macrophages That Heal

After the ADHD Invoice, GPs and Waiters Carry the Cost
-
 NEWS2 months ago
Pennsylvania Measles Deaths Collide With Falling MMR Coverage
-
 FITNESS2 months ago
Muscle-Boosting Drugs Near Approval for Children With SMA
-
 NEWS2 months ago
FDA Approves XFG COVID Vaccines While the Advice Panel Is Frozen
-
 NEWS2 months ago
Progranulin and JAK2 Split the Macrophages That Heal
-
 MENTAL HEALTH2 months ago
After the ADHD Invoice, GPs and Waiters Carry the Cost
-

 NEWS2 months ago
Rasonque’s List Price Shifts the Pancreatic Cancer Bill
-
 NEWS2 months ago
Pennsylvania’s Two Measles Deaths Follow a Long Coverage Slide
-

 NEWS2 months ago
FDA Flagged This Sprout Plant 16 Months Before the Outbreak